
Note: This article is for educational purposes only and should not replace medical advice from a dermatologist, rheumatologist, or other licensed healthcare professional.
Psoriasis has a talent for being dramatic. One day your skin is calm, and the next it acts like it has joined a tiny inflammatory marching band. Red, scaly plaques may appear on the elbows, knees, scalp, lower back, hands, feet, or other areas, often bringing itching, burning, cracking, and the social awkwardness of people asking, “Is that contagious?” Spoiler: it is not.
For many people, mild psoriasis can be managed with moisturizers, prescription creams, medicated shampoos, or light therapy. But when psoriasis becomes moderate to severe, spreads across larger areas, affects sensitive places, or comes with psoriatic arthritis, the treatment conversation changes. That is where biologics enter the roomnot quietly, either. They are among the most important advances in modern psoriasis treatment because they target specific immune signals instead of simply trying to calm the skin from the outside.
So, how are biologics different? The short answer: biologics are targeted immune therapies, usually given by injection or IV infusion, designed to block specific proteins involved in the inflammation that drives psoriasis. The longer answer is more interesting, more practical, and thankfully less itchy.
Understanding Psoriasis Before Understanding Biologics
Psoriasis is a chronic immune-mediated disease. That means the immune system becomes overactive and sends inflammatory messages that speed up the life cycle of skin cells. Instead of shedding normally, skin cells pile up too quickly, forming thick, inflamed, scaly patches called plaques.
While psoriasis shows up on the skin, it is not just a “skin problem.” It can be linked with inflammation throughout the body and may occur with psoriatic arthritis, a condition that causes joint pain, stiffness, swelling, and possible long-term joint damage. Psoriasis can also affect quality of life in very real ways: sleep, confidence, clothing choices, exercise, dating, work, and the simple joy of wearing black without looking like you wrestled a snow globe.
What Are Biologics?
Biologics are medications made from living cells or biological materials. Unlike many traditional drugs that are chemically synthesized, biologics are large, complex molecules designed to interact with very specific parts of the immune system.
In psoriasis treatment, biologics usually target inflammatory proteins called cytokines. These cytokines act like text messages between immune cells. In psoriasis, some of those messages are basically saying, “More inflammation! More skin cell growth! Let’s redecorate the elbows!” Biologics help interrupt those signals.
Most biologics for psoriasis are given as a shot under the skin. Some are given through an IV infusion. Depending on the medication, dosing may happen weekly, every few weeks, every month, or even every few months after starter doses. This can be a major difference from creams that must be applied daily or pills taken more frequently.
How Biologics Differ From Traditional Psoriasis Treatments
1. Biologics Target Specific Immune Pathways
Traditional treatments often work more broadly. Topical corticosteroids reduce inflammation in the skin. Vitamin D analogs help slow skin cell growth. Phototherapy uses controlled ultraviolet light to calm inflammation. Older systemic medications, such as methotrexate or cyclosporine, affect immune activity more generally.
Biologics are different because they aim at specific immune system targets. Instead of using a foghorn to quiet the whole crowd, biologics try to tap the loudest troublemaker on the shoulder.
The main biologic categories used in psoriasis include:
- TNF-alpha inhibitors: These block tumor necrosis factor-alpha, an inflammatory protein involved in psoriasis and psoriatic arthritis. Examples include adalimumab, etanercept, infliximab, and certolizumab pegol.
- IL-17 inhibitors: These target interleukin-17, a key cytokine involved in plaque formation and skin inflammation. Examples include secukinumab, ixekizumab, brodalumab, and bimekizumab.
- IL-23 inhibitors: These block interleukin-23, which helps drive the inflammatory pathway behind psoriasis. Examples include guselkumab, risankizumab, and tildrakizumab.
- IL-12/23 inhibitor: Ustekinumab targets proteins shared by interleukin-12 and interleukin-23.
2. Biologics Are Usually Used for Moderate to Severe Psoriasis
Not everyone with psoriasis needs a biologic. If a small patch on the elbow improves with a prescription cream, there may be no reason to jump to an injectable medication. Dermatologists usually consider biologics when psoriasis is moderate to severe, when it covers a significant body area, when it affects difficult or sensitive areas, or when other treatments have not worked well enough.
Biologics may also be considered when psoriasis seriously affects daily life, even if the total body surface area is not huge. For example, psoriasis on the palms, soles, genitals, face, or scalp can be especially disruptive. A small area can create a big problem when it interferes with walking, working, sleeping, or feeling comfortable in public.
3. Biologics May Help Both Skin and Joints
Some biologics are approved for both plaque psoriasis and psoriatic arthritis. This matters because treating only the skin while ignoring joint inflammation is like fixing the wallpaper while the plumbing is leaking.
For someone with joint pain, morning stiffness, swollen fingers or toes, tendon pain, or nail changes, a dermatologist may coordinate care with a rheumatologist. The treatment choice may depend on whether the main problem is skin plaques, joint inflammation, enthesitis, dactylitis, nail disease, inflammatory bowel disease, or another health factor.
4. Biologics Are Not Daily Creams
Many people are surprised that biologics are not applied directly to plaques. They work from inside the body by changing immune signaling. That can feel strange at first, especially for patients used to rubbing ointment on the visible problem. But psoriasis begins deeper than the surface. The skin is where the immune system’s argument becomes visible.
With biologics, consistency matters. Missing doses can allow symptoms to return. Stopping and restarting should be discussed with a healthcare provider because timing, infection risk, vaccines, surgery, pregnancy plans, and insurance coverage may all affect the treatment plan.
How Effective Are Biologics for Psoriasis?
Biologics can be highly effective for many people with moderate to severe plaque psoriasis. Clinical trials often measure improvement using scores such as PASI 75, PASI 90, or PASI 100, which refer to 75%, 90%, or 100% improvement in psoriasis severity. In everyday language, that means many patients see major clearing, and some approach clear or almost-clear skin.
Effectiveness depends on the specific biologic, the person’s health history, body weight, immune response, adherence, and whether psoriatic arthritis or other conditions are present. Some people respond quickly within weeks. Others need several months to know whether a medication is truly working. A biologic that works beautifully for one person may do very little for another, because immune systems are not copy-paste documents.
Safety: What Patients Should Know
Biologics have changed psoriasis care, but they are still serious prescription medications. Because they affect immune pathways, they can increase the risk of infections. Before starting treatment, healthcare providers often review medical history and may order screening tests. These may include tuberculosis testing, hepatitis screening, blood work, and an update on vaccination status.
Patients should tell their healthcare provider about frequent infections, chronic infections, cancer history, inflammatory bowel disease, multiple sclerosis, heart failure, pregnancy plans, breastfeeding, allergies, and all medications or supplements they take. That list may sound longer than a pharmacy receipt, but it helps match the right medication to the right person.
Live vaccines are generally avoided during many biologic treatments. Inactivated vaccines, such as flu shots, may still be recommended, but timing should be discussed with a clinician. Patients should also contact their healthcare provider if they develop fever, persistent cough, unusual fatigue, painful skin infection, or other concerning symptoms while using a biologic.
Common Side Effects
Side effects vary by medication, but some common ones include injection-site reactions, mild upper respiratory infections, headache, fatigue, or nausea. More serious risks are less common but can include serious infections or allergic reactions. Certain biologic classes may have special warnings. For example, some IL-17 inhibitors may require extra caution in people with inflammatory bowel disease.
This is why choosing a biologic is not just about picking the newest name from a commercial where someone in linen pants hikes near a waterfall. It is a medical decision based on diagnosis, severity, other conditions, risk factors, personal preferences, and practical issues like cost and insurance approval.
Biologics vs. Biosimilars: What Is the Difference?
A biosimilar is a medication that is highly similar to an already approved biologic, known as the reference product. Because biologics are made from living systems and are very complex, biosimilars are not “generic” copies in the same way that a generic tablet is chemically identical to a brand-name pill. Instead, biosimilars must show no clinically meaningful differences in safety, purity, and effectiveness compared with the reference biologic.
For psoriasis and psoriatic arthritis, biosimilars may improve access by creating more treatment options and sometimes lowering costs. Patients may encounter biosimilars for medications such as adalimumab, infliximab, etanercept, or ustekinumab. Whether a biosimilar is available or appropriate depends on the condition being treated, insurance rules, state pharmacy laws, and the prescriber’s recommendation.
Who Might Be a Good Candidate for Biologics?
A person may be a candidate for biologic therapy if they have moderate to severe plaque psoriasis, psoriasis that has not responded well to topical treatment or phototherapy, psoriasis in sensitive or high-impact areas, or psoriatic arthritis. Biologics may also be considered when older systemic medications are not suitable because of side effects, lab abnormalities, drug interactions, or other health concerns.
However, biologics may not be the first choice for someone with an active serious infection, certain untreated infections, or specific medical risks. The decision should come from a detailed conversation with a dermatologist or rheumatologist, not from a social media comment section where “my cousin’s roommate’s barber” has very strong opinions.
What to Expect Before Starting a Biologic
Before prescribing a biologic, a clinician will usually confirm the type and severity of psoriasis, review previous treatments, ask about joint symptoms, check medical history, and discuss treatment goals. They may ask questions such as:
- How much of the body is affected?
- Are plaques painful, itchy, bleeding, or interfering with sleep?
- Are the scalp, hands, feet, nails, face, or genitals involved?
- Is there joint pain, stiffness, swelling, or tendon pain?
- Have topical medications, phototherapy, or oral medications helped?
- Are there infections, immune conditions, pregnancy plans, or vaccine needs?
Insurance approval can also be part of the journey. Some plans require documentation that other treatments were tried first. This process can be annoying, but good dermatology offices are often experienced in prior authorizations, appeals, and patient assistance programs.
How Long Do Biologics Take to Work?
Some patients notice improvement within a few weeks, while others need several months. Dermatologists often evaluate progress after a loading phase or around the three- to four-month mark, depending on the medication. If the response is strong, treatment may continue. If the response is partial, the clinician may adjust the plan, add another therapy, or switch to a different biologic class.
Switching biologics is common and does not mean the patient failed. It means the first medication was not the best match. Psoriasis treatment is less like flipping a light switch and more like tuning a radio: sometimes the signal improves after a few adjustments.
Can Biologics Be Combined With Other Treatments?
Yes, in some cases. A dermatologist may prescribe a biologic along with topical treatments, especially for stubborn plaques on the scalp, hands, feet, or nails. Some patients may also use moisturizers, gentle cleansers, medicated shampoos, or short courses of topical steroids during flares.
Combination therapy should always be supervised. Patients should not mix systemic medications or add immune-altering supplements without medical guidance. “Natural” does not always mean safe, and “I saw it online” is not the same as a treatment plan.
Lifestyle Still MattersEven With Biologics
Biologics can be powerful, but they do not make lifestyle irrelevant. Psoriasis can be influenced by triggers such as stress, skin injury, infections, smoking, heavy alcohol use, cold weather, and certain medications. Maintaining a healthy weight, protecting the skin from trauma, managing stress, sleeping well, and treating infections promptly may support better disease control.
Moisturizing is still useful. Gentle skin care is still useful. Avoiding harsh scrubbing is very useful, unless your goal is to make your plaques angrier than a cat in a bathtub.
The Emotional Side of Starting Biologics
Starting a biologic can feel exciting and intimidating at the same time. Some people worry about injections. Others worry about side effects, costs, insurance, or whether the medication will actually work. These concerns are normal.
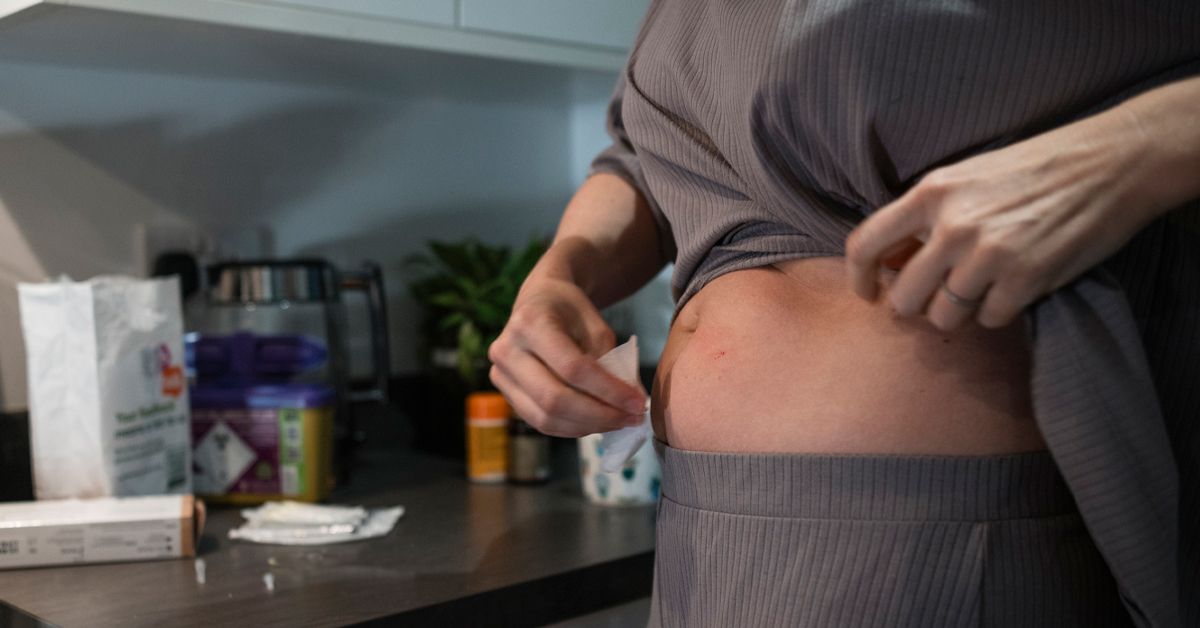
For injection anxiety, many clinics provide training. Some medications come in autoinjector pens. Patients may be taught where to inject, how to store the medication, how to rotate injection sites, and what to do if they miss a dose. Over time, many people find the process less scary than expected. The first injection may feel like a huge event. By the fifth, it may feel like brushing your teeth with slightly more paperwork.
Real-Life Examples of Biologic Treatment Decisions
Example 1: The “Creams Are Not Cutting It” Patient
A patient has plaque psoriasis on the elbows, knees, scalp, and lower back. Prescription creams help a little, but symptoms return quickly. The plaques itch at night and flakes show on dark clothing. If the disease is widespread or quality of life is significantly affected, a dermatologist may discuss biologics as an option.
Example 2: The “My Hands and Feet Are a Problem” Patient
Another patient has psoriasis mainly on the palms and soles. The affected area is not huge, but walking hurts, typing is uncomfortable, and cracks bleed. Even though the body surface area may be limited, the functional impact is high. A biologic may be considered if other treatments fail.
Example 3: The “Skin Plus Joints” Patient
A person has plaques and morning stiffness in the fingers. They also notice nail pitting and swollen toes. This raises concern for psoriatic arthritis. A treatment that addresses both skin and joints may be preferred, and a rheumatology evaluation may be important.
Questions to Ask Your Doctor About Biologics
- Which biologic class fits my symptoms best?
- Do I have signs of psoriatic arthritis?
- What tests do I need before starting?
- How soon should I expect improvement?
- What side effects should I watch for?
- Can I take vaccines before or during treatment?
- What happens if this biologic does not work?
- Is there a biosimilar that could lower my cost?
- How should I store and travel with the medication?
Added Experience Section: What Living With Biologic Treatment Can Feel Like
For many people, the experience of starting a biologic begins long before the first dose. It often starts with frustration. They have tried thick ointments that stain pajamas, shampoos that smell like a science project, creams that work until they suddenly do not, and lifestyle changes that help but do not fully control the condition. By the time biologics enter the conversation, many patients are not casually browsing treatment options. They are tired.
One common experience is the emotional weight of being seen. Psoriasis can make people hyper-aware of their skin. They may choose long sleeves in summer, avoid swimming, skip haircuts, or worry about flakes on office chairs. When a dermatologist says, “This is moderate to severe, and you have more options,” it can feel validating. The problem is not laziness, poor hygiene, or lack of willpower. It is immune-driven inflammation, and it deserves real treatment.
The next experience is usually paperwork. Biologics can be expensive, and insurance approval may require records of previous treatments. Patients may need photos, chart notes, lab results, or proof that topical therapy or phototherapy was not enough. This stage can feel like psoriasis has hired an accountant. Still, persistence matters. Many clinics have staff who handle prior authorization, manufacturer assistance programs, or biosimilar substitution questions.
Then comes the first injection or infusion. Some people are nervous, especially if they dislike needles. Autoinjector pens can make the process simpler, but the first dose may still feel dramatic. Patients often learn practical habits: remove the medication from the refrigerator as instructed, choose a comfortable injection site, rotate locations, avoid irritated skin, and keep a calendar reminder. Small routines reduce stress. A dose tracker is not glamorous, but neither is forgetting whether the last shot was two weeks ago or during the previous presidential administration.
Improvement can feel gradual or surprisingly fast. Some patients first notice less itching. Others notice plaques becoming flatter, thinner, or less red. Scalp flakes may decrease. Sleep may improve. Clothing choices may expand. Someone may suddenly realize they wore a black shirt without checking their shoulders every ten minutes. These small wins can feel enormous because psoriasis often takes up more mental space than outsiders understand.
Not every experience is perfect. Some patients get only partial improvement. Some develop side effects. Some medications lose effectiveness over time. Others are interrupted by infections, surgery, insurance changes, pregnancy planning, or travel. A biologic is not a magic wand; it is a tool. But for the right patient, it can be a very good toolmore power drill than plastic spoon.
Another real-life issue is explaining biologics to family or friends. People may hear “immune medication” and worry. A simple explanation helps: biologics do not shut off the entire immune system; they target specific inflammatory signals involved in psoriasis. Still, infection precautions are important, and medical follow-up matters. Patients should feel comfortable asking questions and reporting symptoms without feeling like they are bothering anyone.
Long-term, the best experience often comes from partnership. Patients who do well usually communicate openly with their care team, attend follow-up visits, keep up with recommended labs or screenings, and speak up when goals are not being met. Clear skin may be one goal, but so is less itching, better sleep, improved confidence, reduced joint pain, and fewer flares. Good psoriasis care is not only about what the skin looks like in a clinic room. It is about how life feels outside that room.
Conclusion: Biologics Are Different Because They Treat Psoriasis at Its Immune Source
Biologics are different from many traditional psoriasis treatments because they target specific immune pathways that drive inflammation. Instead of only treating visible plaques from the outside, biologics work inside the body to interrupt signals such as TNF-alpha, IL-17, IL-23, or IL-12/23. For people with moderate to severe psoriasis, hard-to-treat areas, or psoriatic arthritis, they can be life-changing.
They are not casual medications, and they are not right for everyone. They require screening, monitoring, good communication, and a realistic discussion about benefits, risks, cost, dosing, and long-term goals. But for many patients, biologics have turned psoriasis treatment from “manage the mess” into “control the disease.” That is a major shiftand a welcome one.
If psoriasis is interfering with sleep, movement, confidence, work, relationships, or daily comfort, it may be time to talk with a dermatologist about whether biologics or biosimilars belong in the treatment conversation. Your skin may be loud, but modern medicine has learned a few ways to lower the volume.