
Doctors are trained to spot the tiny clue everyone else misses. A subtle murmur. A weird lab trend. A patient saying, “I’m fine,” while looking like a walking discharge summary. Yet when it comes to financial independence, many physicians miss the biggest clue of all: a high income is not the same thing as freedom.
That sentence should be printed on every new attending’s first paycheck, preferably in large red letters next to the taxes. Medicine creates an unusual financial timeline. Doctors spend their twenties and sometimes part of their thirties studying, borrowing, training, working long hours, delaying retirement savings, and telling themselves, “It will all be fine when I’m making real money.” Then real money arrives, wearing a white coat and carrying a mortgage application, a luxury SUV brochure, a private school tour schedule, and a spouse who has also been waiting twelve years to stop living like a raccoon in fluorescent hospital lighting.
The common physician belief is simple: “I worked hard, I earn a lot, therefore financial independence will take care of itself.” That belief is dead wrong. Not mildly wrong. Not “needs a small correction” wrong. It is wrong in the same way that wearing Crocs to a black-tie wedding is technically footwear but spiritually alarming.
Financial independence for doctors is not about quitting medicine tomorrow, selling everything, and moving to a cabin with suspicious Wi-Fi. It is about owning your time, your choices, and your professional future. It means you can reduce call, leave a toxic job, say no to a bad contract, support your family, recover from burnout, or continue practicing because you love the worknot because your lifestyle has you trapped like a golden handcuff with a stethoscope attached.
The Biggest Mistake: Confusing Income With Wealth
Physicians often earn strong incomes compared with many other professions, but wealth is not what comes in. Wealth is what stays, grows, and gives you options. A doctor making $400,000 a year and spending $410,000 is not rich. That doctor is just operating a very fancy financial treadmill.
This is where the physician brain can get tricked. In medicine, achievement tends to be linear: study more, score higher, match better, work harder, become attending. Money does not always work that way. You can work extremely hard and still end up behind if your spending expands faster than your net worth. A high salary can hide bad habits for years, the way a white coat hides a coffee stain until the exact moment you walk into grand rounds.
Financial independence is built on the gap between income and spending. The wider the gap, the faster the path. Doctors usually focus on the income side because that part feels obvious. They negotiate salary, pick specialties, add shifts, moonlight, or chase productivity bonuses. But the spending side quietly decides whether that income becomes freedom or just nicer furniture.
The Delayed Start Problem Doctors Underestimate
Many professionals begin earning, saving, and investing in their early twenties. Doctors often start later because medical school, residency, and fellowship delay peak earnings. During those years, loans may grow, retirement contributions may be small, and life milestones are postponed. By the time the attending paycheck arrives, the doctor is not starting at zero. In many cases, the doctor is starting below zero with a long list of delayed wants.
This delayed start matters because compounding rewards time. Money invested at 25 has decades to work. Money invested at 38 still has power, but it needs more discipline. The solution is not panic. The solution is honesty. A physician cannot use the same casual savings strategy as someone who started a stable career fifteen years earlier and expect the same result.
Doctors are excellent at delayed gratification during training. Then the attending years arrive and, understandably, the emotional bill comes due. After years of cafeteria dinners, secondhand furniture, and sleeping near a pager like it is a needy electronic hamster, doctors want the good life immediately. The problem is not wanting comfort. The problem is upgrading every category at once: house, car, vacations, dining, wardrobe, childcare, schools, gadgets, hobbies, and “just one small boat,” which is usually how financial horror movies begin.
Lifestyle Creep Is the Silent Attending-Level Disease
Lifestyle creep is what happens when spending rises automatically with income. It rarely feels dramatic. Nobody wakes up and announces, “Today I shall sabotage my financial independence with artisanal tile.” It happens one reasonable purchase at a time.
A bigger house seems reasonable because the family needs space. A nicer car seems reasonable because the commute is exhausting. Expensive vacations seem reasonable because burnout is real. Private school seems reasonable because education matters. A country club seems reasonable because networking exists. Before long, the doctor has built a beautiful life that requires full-time attending income forever. That is not independence. That is dependency wearing a cashmere sweater.
The most dangerous expenses are not always the flashy ones. Fixed monthly obligations are the real trap: mortgage payments, car payments, private school tuition, insurance, club dues, staff, subscriptions, and lifestyle expectations that become emotionally difficult to reverse. A one-time splurge may sting. A permanent monthly obligation changes the entire shape of your future.
The “I Deserve It” Argument
Doctors do deserve good things. They deserve rest, comfort, safety, joy, and a life outside the hospital. But “I deserve it” is not a financial plan. It is a feeling. Feelings are important, but they should not be allowed to drive the household budget without adult supervision.
The healthier approach is not deprivation. It is intentional luxury. Spend generously on what truly improves your life. Cut ruthlessly on what merely impresses people you barely like. A physician who loves travel can build a plan around travel. A physician who values living near work may choose a better location. A physician who wants help at home may pay for cleaning or childcare. The key is choosingnot blindly upgrading everything because the paycheck finally looks impressive.
Doctors Often Think Financial Independence Means Retirement
Another major misunderstanding is that financial independence equals early retirement. For some doctors, yes, it may mean leaving clinical medicine early. For many others, it means practicing differently. It means choosing the work rather than being cornered by it.
A financially independent physician can reduce to four days a week, take fewer night shifts, switch to teaching, open a smaller practice, do mission work, move closer to family, take a sabbatical, or walk away from an abusive employer. That freedom may save a medical career rather than end it.
Doctors often say, “I don’t want to retire early; I love medicine.” Wonderful. But loving medicine does not require financial vulnerability. You can love your profession and still want the power to say no. In fact, doctors who do not need every dollar may become better negotiators, better advocates, and sometimes better clinicians because fear is no longer silently making career decisions for them.
The Burnout Connection: Money Is Not Just Money
Physician burnout is usually discussed in terms of workload, administrative burden, electronic health records, staffing shortages, moral injury, and lack of autonomy. All of those matter. But money also plays a rolenot because doctors are greedy, but because financial pressure reduces choices.
A burned-out doctor with no debt, strong savings, and a flexible lifestyle has options. A burned-out doctor with huge fixed expenses may feel trapped. That trapped feeling can turn a difficult job into a psychological cage. The paycheck becomes both medicine and poison: necessary for survival, but tied to the very stress that is making life harder.
Financial independence is therefore not only a retirement goal. It is a wellness strategy. Emergency funds, disability insurance, sane debt management, retirement contributions, and controlled spending are not boring adult chores. They are emotional shock absorbers. They give a physician room to breathe when the job becomes heavy.
Student Loans Need a Strategy, Not Vibes
Many doctors leave training with significant education debt. The wrong approach is pretending the loans are just background noise. The other wrong approach is attacking every loan with such intensity that retirement investing, emergency savings, and life itself get ignored.
Student loan planning depends on specialty, income, employer type, interest rates, family goals, tax situation, and eligibility for forgiveness programs. A physician working for a nonprofit hospital may have a very different strategy from a private practice dermatologist or an independent contractor emergency physician. The point is not that every doctor should repay loans the same way. The point is that every doctor needs a written plan.
Without a plan, loans become emotional fog. Doctors may refinance too early, miss forgiveness opportunities, under-save for retirement, or carry expensive debt while spending freely elsewhere. A good plan answers basic questions: Are we pursuing forgiveness? Are we refinancing? What is the payoff timeline? How much goes to retirement while loans remain? What happens if income changes?
The First Five Attending Years Are Financially Sacred
The first few years after training can change everything. This is when income often jumps dramatically, and the temptation to upgrade life is strongest. It is also the best window to build lasting financial momentum.
One of the most powerful strategies is to “live like a resident” for a limited period. That does not mean eating instant noodles under a flickering light while wearing socks with holes. It means allowing lifestyle to rise slowly while directing a large portion of the new attending income toward debt repayment, investments, emergency savings, insurance, and future goals.
Even two or three disciplined years can create a powerful base. Loans shrink. Retirement accounts grow. Cash reserves appear. The doctor learns that a high income can produce wealth if it is not immediately absorbed by lifestyle inflation. After that base is built, spending can increase more safely because the financial engine is already running.
Financial Independence Requires a Personal Policy Statement
Doctors live by protocols. Chest pain protocol. Sepsis protocol. Stroke protocol. Yet many run their financial lives with the strategy of “we’ll see what happens,” which is not a protocol; it is a shrug wearing a lab coat.
A personal financial policy statement does not need to be complicated. It should include your savings rate, debt plan, investment approach, insurance needs, housing limits, giving goals, and target timeline for financial independence. The purpose is to make decisions before emotions take over.
For example, a physician couple might decide: “We will save 25% of gross income, max available retirement accounts, maintain six months of expenses in cash, avoid buying a home that requires both incomes at full strength, and invest in low-cost diversified funds.” That statement is simple, but it prevents dozens of future arguments and impulsive choices.
The House Can Make or Break the Plan
For many physicians, the home purchase is the financial independence turning point. A doctor mortgage can make buying easy, sometimes too easy. The bank may approve a large loan because the income looks strong. Approval is not the same as wisdom. A lender asks, “Can you technically pay this?” Financial independence asks, “Can you pay this and still own your life?”
A house that fits comfortably within one income or a reduced schedule creates flexibility. A house that requires constant high earnings creates pressure. The same applies to renovations. Kitchens have a magical ability to turn into financial sinkholes with better lighting. Nobody starts by saying, “Let’s spend the equivalent of a fellowship year on cabinets.” And yet, here we are.
Doctors should be especially cautious about buying the dream home immediately after training. Renting for a year, understanding the job, learning the neighborhood, and stabilizing finances can prevent expensive regret. The dream home is less dreamy when paired with a job you hate and a commute that makes you question the meaning of existence.
Investment Complexity Is Overrated
Physicians are smart, which unfortunately makes them attractive targets for overly complex financial products. If someone sees “MD” after your name, there is a decent chance they also see “potential buyer of confusing things with high fees.” Whole life insurance sold as an investment, private deals you do not understand, speculative real estate partnerships, and exotic tax shelters can all appear sophisticated. Sophisticated does not always mean good.
Most doctors do not need a financial circus. They need high savings, tax-efficient accounts, reasonable insurance, diversified investments, estate planning, and discipline. The boring plan often wins because it is easy to follow during busy weeks, market downturns, and emotionally chaotic seasons.
The best investment strategy is one you understand well enough to stick with when headlines get dramatic. If your portfolio requires a secret decoder ring and a dinner meeting at a steakhouse, pause. Complexity should earn its place. Otherwise, simplicity is not a weakness. It is a feature.
Financial Independence Is a Team Sport
For married or partnered physicians, money cannot be treated as one person’s hobby. The non-physician spouse may have carried years of sacrifice during training. They may reasonably want a better lifestyle now. Ignoring that emotional reality is a recipe for resentment, not wealth.
The conversation should not be, “We can’t spend anything because a spreadsheet said so.” The better conversation is, “What do we want our money to do for our family?” Maybe the family wants flexibility, time with children, travel, generosity, safety, or the option to leave a difficult job. Once the shared vision is clear, the budget becomes less like punishment and more like a map.
Children also influence the plan. Childcare, school, college savings, housing, and time all matter. A financially independent doctor is not necessarily the doctor with the largest account balance. It may be the doctor who built a life where money supports family values instead of constantly competing with them.
The Correct Way Doctors Should Think About Financial Independence
The right mindset begins with a new definition: financial independence is the point at which work becomes optional, flexible, or chosen on your terms. It is not a number alone. It is a relationship between assets, spending, risk, and personal meaning.
Doctors should ask better questions. Not “Can I afford this?” but “What does this purchase do to my future choices?” Not “When can I retire?” but “When can I practice without fear?” Not “How much do I make?” but “How much of my income becomes durable freedom?”
A doctor who earns less but saves consistently may become independent faster than a higher-earning colleague with runaway expenses. A primary care physician with a modest home, good benefits, and steady investments may be financially stronger than a specialist with twice the income and five times the obligations. In medicine, the biggest paycheck does not always win. The best system wins.
A Practical Physician Financial Independence Framework
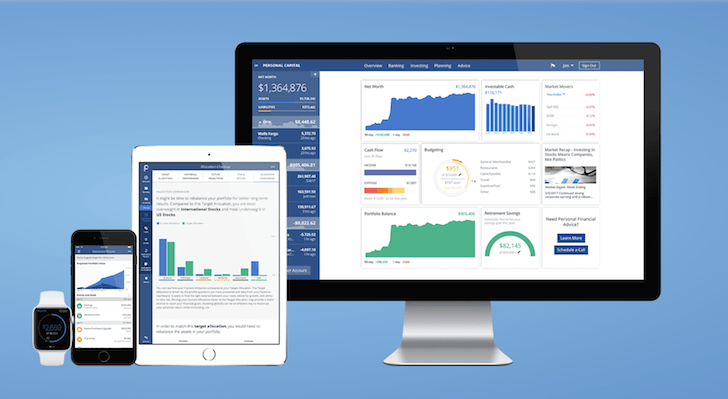
1. Build a One-Page Net Worth Dashboard
Track assets, debts, cash, investments, and insurance coverage. Review it monthly or quarterly. Doctors love data. Use that strength on your own financial chart.
2. Create a Written Student Loan Plan
Decide whether you are pursuing forgiveness, refinancing, or aggressive repayment. Do not let loans drift in the background like an unclosed chart from last Tuesday.
3. Save a Serious Percentage of Income
Many physicians need a higher savings rate than the average worker because they start later and earn more. A strong savings rate can turn a delayed start into a powerful comeback.
4. Control Fixed Costs
Housing, cars, schools, and recurring commitments determine flexibility. Keep fixed costs low enough that a career change, health issue, or reduced schedule would not destroy the plan.
5. Protect the Income Engine
Disability insurance, term life insurance when others depend on your income, emergency savings, and malpractice awareness are essential. Your income is a major asset. Protect it before chasing shiny investments.
6. Invest Simply and Consistently
Use diversified, low-cost investments that match your risk tolerance and timeline. Avoid investments you cannot explain without sweating.
7. Reclaim Time Gradually
Financial independence is not all-or-nothing. Use progress to buy back time: fewer extra shifts, better vacations, reduced call, or more control over your schedule.
Conclusion: The Dead-Wrong Belief Must Go
The dead-wrong belief is that doctors automatically become financially independent because they earn high incomes. In reality, physicians face a strange mix of delayed earnings, heavy debt, intense burnout risk, lifestyle pressure, and complex career decisions. A large paycheck helps, but it does not replace planning.
The doctors who win financially are not always the highest earners. They are the ones who convert income into options. They resist the urge to upgrade everything at once. They make student loan decisions intentionally. They protect their income, invest steadily, avoid unnecessary complexity, and define success beyond status.
Financial independence is not anti-medicine. It may be one of the best ways to preserve a meaningful medical career. When doctors no longer practice from fear, debt, or lifestyle pressure, they can choose work with clearer minds and healthier boundaries. That is good for physicians, families, and patients.
So yes, enjoy the attending paycheck. Buy the good mattress. Take the vacation. Replace the residency couch that has seen things no furniture should witness. But do not confuse spending with freedom. The goal is not to look rich in the hospital parking lot. The goal is to own your time before your calendar, mortgage, and call schedule own you.
Experience Notes: What This Looks Like in Real Physician Life
The most common physician financial independence story does not begin with a dramatic disaster. It begins with a doctor saying, “We’re doing fine.” And technically, they are. The bills are paid. The income is strong. The family has a nice home. The vacations are good. The retirement accounts exist. Nothing is on fire, except maybe the doctor’s nervous system after seven portal messages marked “urgent” but containing the phrase “mild toenail concern.”
Then something changes. The doctor starts dreading Mondays. A new administrator arrives with a gift basket full of productivity targets. The electronic health record adds seventeen clicks to a task that already felt like punishment. A parent gets sick. A child needs more time. The doctor wants to reduce hours, but the household budget says, “Absolutely not, bestie.” That is when the difference between income and independence becomes painfully clear.
One physician experience that comes up again and again is the emotional whiplash after training. During residency, everyone talks about survival. After training, everyone talks about catching up. Catching up on sleep. Catching up on family time. Catching up on nice clothes, reliable cars, decent food, and living somewhere that does not have a mystery stain on the ceiling. None of those desires are foolish. The danger is trying to catch up financially and emotionally by spending the entire attending raise before it has a chance to build stability.
A young attending might buy the large house immediately, partly because it feels like proof that the sacrifice was worth it. Another might lease the luxury car because, after years of driving something that made a concerning noise near every intersection, reliability feels sacred. A third might say yes to every family request because guilt from years of absence is powerful. These are human choices, not moral failures. But when all of them happen together, the doctor’s new income disappears with shocking speed.
The doctors who seem happiest with their financial lives often make one quiet decision early: they separate celebration from permanent obligation. They celebrate finishing training, but they do not instantly lock themselves into expenses that require maximum income forever. They take a vacation, but they do not buy a vacation house. They upgrade the car, but not to a payment that looks like a second mortgage wearing leather seats. They improve their lifestyle, but slowly enough that savings and debt repayment get first claim on the new income.
Another real-world lesson is that financial independence changes how doctors behave at work. A physician with savings can ask better questions during contract negotiations. They can challenge unsafe expectations. They can leave a job that damages their health. They can take time off after a difficult season without needing to calculate whether the family can still make every payment. That kind of freedom is not visible on social media, but it is deeply valuable.
There is also a relationship lesson. Many physicians assume the financial plan is obvious because the math is obvious to them. But money is never only math. A spouse may hear “save aggressively” as “keep sacrificing forever.” A doctor may hear “let’s enjoy life” as “ignore the future.” The best physician families turn financial independence into a shared project. They choose what they are saving for: time, safety, generosity, travel, career flexibility, or peace. Once the goal has a human face, the plan becomes easier to follow.
The final experience is the most encouraging one: doctors can recover from a late start. They do not need perfection. They need direction. Even physicians who made expensive early mistakes can improve quickly because strong income gives them a powerful tool. Selling the too-expensive car, refinancing wisely, downsizing expectations, automating investments, and setting a real savings rate can transform the situation within a few years. The best time to start was probably during residency. The second-best time is before the next lifestyle upgrade sneaks into the house carrying a catalog and a very convincing smile.
Note: This article is for educational content and general financial discussion only. Physicians should consult qualified tax, legal, insurance, and financial professionals before making personal financial decisions.